A model can render a convincing next surgical scene and still be wrong about tissue, occluded anatomy, instrument contact, or camera delay. For developers, that output is a hypothesis to test—not a clinical instruction.
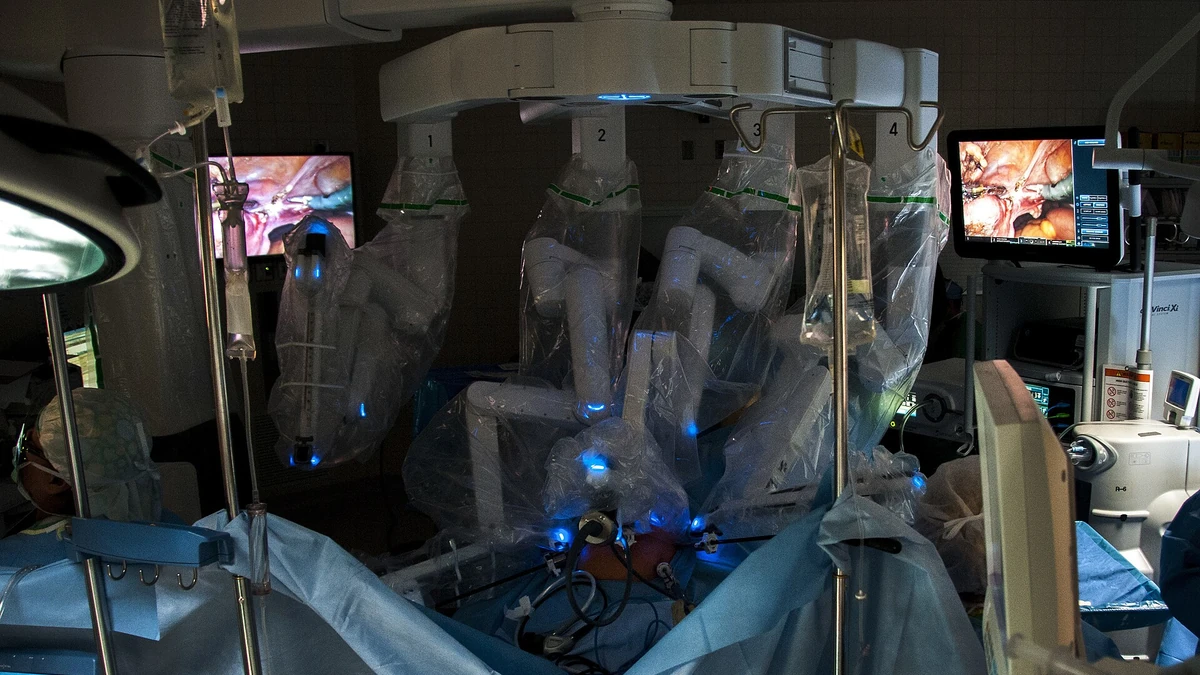

CMR Surgical’s SRS 2026 disclosure is explicit: the Cosmos-H-Dreams connection is a research demonstration, is not part of the currently cleared Versius Plus system, and is not intended for clinical decisions or patient care. Those negations define the article’s safety and regulatory boundary.
The job is to test an action before physical execution
The disclosed workflow takes a current surgical scene and a proposed robot action and predicts what the field might look like afterward. That can help developers explore candidate actions without first applying them to a patient. It does not select the clinically correct action, authorize execution, or replace the surgeon, the device controller, or the cleared instructions for use. A future image is a model output whose assumptions must be visible. Predicting a scene and choosing a treatment are different jobs.
What CMR and NVIDIA each contribute
Versius Plus supplies the robot geometry and surgical context. CMR says Cosmos-H-Dreams was adapted using Open-H-Embodiment data and NVIDIA Cosmos world foundation models, with NVIDIA Isaac for Healthcare providing a broader medical-physics simulation setting. The differentiator is not the model name alone; it is whether instrument geometry, camera view, tissue deformation, and contact assumptions correspond to the physical system. See the world-model boundary for why generated video and validated dynamics are different. A simulation stack is only as useful as its physical and data correspondence.
The immediate customer is a development and validation team
At this stage, developers and verification specialists—not patients—are the direct users. They can create rare, hazardous, or difficult-to-repeat scenarios, compare proposed-action outcomes, and enlarge a failure set. Simulation cannot eliminate bench, phantom, animal-model, or other applicable real-world validation. Blood, smoke, lens contamination, occlusion, and tissue variability can create a reality gap that a visually plausible scene conceals. Rare-case generation increases coverage but not automatically validity.
Compare simulation with the other evidence routes
Retrospective surgical video provides real clinical context but cannot show the counterfactual result of an action that was never taken. Physical models provide real contact but make rare conditions expensive to reproduce. Generative simulation can produce many action-conditioned scenes quickly but inherits model bias and uncertain physics. A sensible program uses each method for a defined question and cross-checks their disagreements instead of naming one universal substitute. Each alternative exposes a different class of error.
| Evidence route | What it contributes | What remains unresolved |
|---|---|---|
| Retrospective video | Real clinical scenes | Outcome of unexecuted actions |
| Physical or bench model | Instrument contact and measurable geometry | Rare-event scale and full tissue realism |
| Cosmos-H-Dreams research simulation | Rapid action-conditioned future scenes | Model bias, physics error, and clinical validity |
Data lineage becomes a supplier dependency
Model behavior depends on which procedures, instruments, viewpoints, tissues, and events appear in the training and adaptation data. A change to that data or to a base model can change the same future-scene prediction. Versioned datasets, documented exclusions, a reproducible test set, execution hardware, latency limits, uncertainty display, and an update-approval owner are therefore part of the product dependency—not housekeeping around it. Medical change control must bind model, data, hardware, and use context.
Keep cleared surgery and research prediction in separate ledgers
CMR states that Versius Plus received US 510(k) clearance for robot-assisted cholecystectomy in adults aged 22 and older. At the announcement, gynecologic indications including benign total hysterectomy were under review. Neither status clears Cosmos-H-Dreams. The demonstration also supplies no hospital deployment, patient-outcome improvement, autonomous-surgery rate, or independent clinical performance result.
Regulatory status belongs to a specific device function and indication.
| Component | Public status | Do not infer |
|---|---|---|
| Versius Plus | 510(k) for a stated adult cholecystectomy use | Clearance for every procedure |
| Cosmos-H-Dreams link | SRS 2026 research demonstration | Current clinical function |
| Open-H-Embodiment and Cosmos | Adaptation basis described | Generalization to all anatomy and actions |
| Hospital deployment | No result published for this feature | Improved patient outcomes |
Demand error distributions before clinical claims
Validation should stratify error by tissue, instrument, camera occlusion, smoke, bleeding, and lens contamination. Add counterfactual actions that should be rejected and measure whether the system abstains rather than confidently inventing a safe-looking scene. Human-factors testing must show that users recognize a simulated, unexecuted hypothesis, can inspect its source and version, and do not mistake realism for clinical certainty.
No clinical efficacy or patient-safety improvement was published for this research feature.
- research labeling
- execution lockout
- audit trail
- current-scene provenance
- proposed-action encoding
Questions readers ask next
What does Cosmos-H-Dreams generate from a current surgical scene and a proposed action, and why is that output not authorized autonomous surgery?
No. CMR labels the connection as research and demonstration work, not part of the currently cleared Versius Plus feature set and not intended for clinical decisions or patient care. No hospital deployment of this function is established by the release.
Which error sets, human-factors studies and model-change controls would be required before future-scene prediction could inform clinical use?
No. The demonstration generated a possible future scene after a proposed action. Autonomous-surgery evidence would require defined control authority, error rates across real and simulated conditions, human supervision, safe-stop behavior, multi-site reproducibility, regulatory review, and clinical outcomes.
Official source trail: